I used to ask every new dialysis patient the same thing — "What was your A1C before your kidneys failed?" After 11,000 patients and the same answer every single time, I stopped asking. It was always "managed." It was always between 6.5 and 7.5. It was always someone who did everything their doctor told them to do. The chairs aren't full of people who ignored their blood sugar. They're full of people who trusted the wrong number.
I need to tell you something I've been carrying for a long time. And I'm telling you now because last month I got my own prediabetes diagnosis — and I refuse to end up in one of my own chairs.
I'm Sandra Keller. I've been a dialysis nurse for 14 years. Roughly 11,000 patients connected to machines.
Let me tell you what that actually looks like — because most people only know the word. They don't know the room.
Three days a week. Four hours a session. A needle goes into a fistula — a surgically created access point in the arm that leaves a scar most patients hide under long sleeves even in summer. The machine pulls their blood out, cleans it — does what their kidneys cannot anymore — and pushes it back in. For four hours. While they sit there.
I've watched people cry during sessions — not from pain but from the weight of what their life became.
I've watched a 61-year-old man read the same magazine in the waiting room every Tuesday and Thursday for three years while his wife was connected.
I've watched patients stop traveling because they cannot miss a session.
I've watched marriages buckle under the schedule.
I've watched grandchildren learn to plan around Grandma's dialysis days — "we can't do Saturday, Grandma has her treatment."
I've watched patients stop coming. And I know what that means.
One of my long-term patients — a woman named Ruth, 63, three years in my unit — told me something I think about every single day. She said: "This isn't living. This is just not dying yet."
And you know what every single one of them says when I ask how they got here?
"I did everything right. My blood sugar was managed. Nobody told me my kidneys were dying."
Every. Single. One.
Last month I sat in my own doctor's office and heard the word "prediabetes" attached to my name.
A1C: 6.4. Fasting glucose running 135 to 145.
And here's the part that made my hands go cold — my creatinine had crept from 0.8 to 1.0 over ten months. My GFR — the number that tells you how well your kidneys are actually filtering — had dropped from 98 to 86.
On paper, none of that is alarming. My doctor said "we'll keep an eye on it."
But I've heard those exact words before. I've heard them from the charts of people who are now sitting in my chairs. I know what "keeping an eye on it" looks like from the other end. It looks like quarterly labs that document the decline in neat little rows while the kidneys quietly fall apart between appointments.
I know what a creatinine of 1.0 looks like at the beginning. Because I've held the hands of people whose creatinine started at 1.0.
And I felt something I'd never felt in 14 years of nursing — real, bone-deep terror. Not for my patients. For myself.
Two weeks later, something happened that changed the direction of everything.
A patient came into my unit for his session. Type 2 for twelve years. On dialysis for nineteen months. I'd known him the whole time. He pulled a bag out of his jacket and set it on the table next to his chair.
"Sandra. Tell your people about this."
I picked it up.
Ceylon cinnamon. Concentrated extract. 7,200mg equivalent in MCT oil.
Called Metabolae.
"My brother-in-law started taking it four months ago. A1C was 7.2. Now it's 5.9. His kidneys haven't gone further down. He was headed where I am. Not anymore."
He looked at me.
"My brother-in-law is not sitting in one of these chairs. And he was supposed to be."
I took the bag home that night.
I did what I've done my whole career when something doesn't add up. I opened my laptop at 11:30 PM and started reading.
Here is what I found. And here is the thing I should have learned years earlier.
Your A1C measures one thing: the percentage of your red blood cells coated in glucose. It's a rolling 90-day average of how much sugar is floating in your blood.
That is all it measures.
It does not see what that sugar is doing while it circulates. It does not see the tiny capillaries threading through your kidney tissue. It does not see the small vessels feeding the nerves in your feet. It does not see the delicate blood supply behind your eyes.
It sees the level of the flood.
Not where the flood is going.
A 6.4 can be called prediabetic and your kidney filters can still be quietly wearing down behind it. A 6.8 can be called "managed" and the decline keeps moving. Both things are completely true at the same time. Because the A1C is tracking the water level. Your kidneys are paying the price of the current underneath.
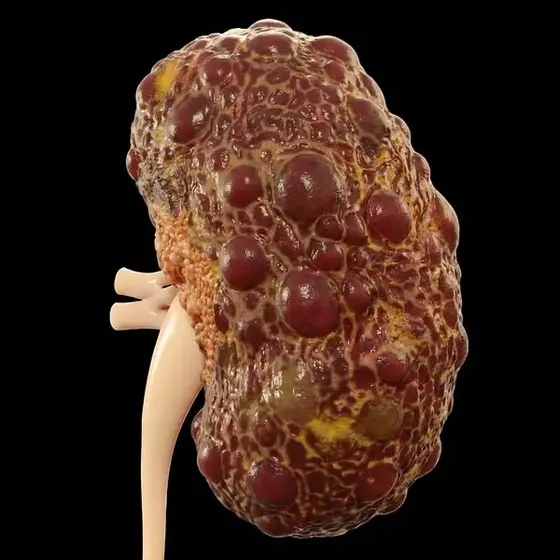
This is what produces foam in your toilet. The tiny filters inside your kidneys — glomeruli — have been under sustained pressure from glucose circulating through their walls for years. They start to fail. Protein leaks out. It shows up in your urine as foam that sits there after you flush.
That foam is not a warning sign that something might happen.
It is evidence that something is already happening.
Let me explain the mechanism underneath — because once you see it, you'll understand why "managed" doesn't mean "safe."
Every cell in your body has tiny doors on its surface — protein transporters called GLUT4. Their job is to open up, grab glucose from the blood, and pull it inside the cell where it gets converted to energy.
In a healthy body, insulin gives the signal, the doors open, glucose moves from blood into cell, and blood sugar comes down.
In insulin resistance — the thing underneath type 2 diabetes — those doors stop responding.
They're still there. They just stopped coming to the surface. Insulin gives the signal. Nothing happens. Your pancreas sends more insulin. Still nothing. The glucose has nowhere to go, so it stays in your blood and keeps circulating.
Your cells are starving.
Your blood is flooded.
And the sugar floating through your bloodstream keeps passing through every small blood vessel in your body, hour after hour, year after year, wearing the walls down from the inside.
Think of your kidneys like the finest mesh screen you've ever seen — millions of tiny filters. That excess sugar is like fine sand being forced through the mesh under pressure.
Hour after hour. Day after day. Month after month. The mesh starts to tear. First it leaks a little protein — that foam. Then the tears get bigger. Then the filtration rate drops. Then the whole system starts to fail.
Metformin slows the flow of sand a little.
But the sand is still coming. And the mesh is still tearing. And the monitoring? The monitoring just measures how torn the mesh is getting. Nobody is stopping the sand.
And it is not just the kidneys.
That same sugar pileup strips the insulation off your nerves — that's why your feet burn and your hands tingle.
It starves your brain of fuel — that's why the fog rolls in by 2pm and the words get lost. It wrecks the tiny blood vessels behind your eyes — that's why the floaters showed up.
It locks your body in fat-storage mode — that's why the belly won't budge. It shatters your sleep — that's why you're up three times a night with a racing heart.
And it damages the blood vessels responsible for intimacy — that's why that part of your life quietly disappeared and nobody connected it to blood sugar.
All of it — kidneys, nerves, brain, eyes, sleep, weight, intimacy — traces back to the same closed doors.
Your doctor monitors the headline number. The story underneath it is your organs falling apart.
Now — your medications.
Metformin works on the input side of this problem. It tells your liver to produce less glucose. It reduces the flood. That is a real, useful thing and your doctor is not wrong to prescribe it.
But it does not touch the doors.
The GLUT4 transporters are still not responding. The glucose that remains in your blood — even at a "managed" level — keeps circulating. Keeps passing through your kidney capillaries. Keeps grinding the mesh. Because the drug that reduced the flood did not open the drain.
And here is what stopped me cold at 2 AM in my kitchen with 14 years of dialysis nursing behind me:
The research on how to open those doors exists.
It has been published. Peer-reviewed. Cited by the ADA's own journals. Sitting in databases that a 15-minute appointment leaves no time to read.
There is a specific compound that triggers GLUT4 transporters directly. It bypasses the broken insulin signal entirely. It goes to the cell, speaks to the machinery inside it, and wakes the doors back up.
A 2003 study in Diabetes Care — the ADA's own flagship journal — showed these compounds produced a 29% drop in fasting blood glucose.
A study published in the Journal of the American College of Nutrition found that MHCP triggers the same internal chemical cascade that insulin is supposed to trigger, and was 20 times more effective at activating this pathway than any other natural compound tested.
Twenty times.
A second study in the Archives of Biochemistry and Biophysics confirmed that Ceylon extract physically increases the number of GLUT4 transporters at the cell surface. The doors do not just crack open. They multiply.
A 2012 review in the Journal of Medicinal Food analyzed eight randomized controlled trials and found meaningful drops in both fasting glucose and A1C.
Published. Replicated. Real.
And in 14 years of working at the end of the road — watching thousands of patients get pulled into those chairs — not once had anyone put this in my hand.
Not because doctors are hiding it.
Because the pipeline that moves research from a journal into a treatment room runs on patent money.
You cannot patent a plant.
So no pharmaceutical company funds the trials that would land it on a sales representative's desk. No sales rep walks it into a primary care office. The studies stay in databases. The patients keep coming in with foam in their toilets and GFRs that drop another point each quarter.
That is not your fault.
You took the pills. You tracked the number. You kept every appointment. You were not failing the system. The system was only giving you half the answer and never telling you the other half existed.
Now. You have probably tried cinnamon before. You sprinkled it on oatmeal. You found a bottle at the grocery store or on Amazon and took it faithfully for three months and watched your meter not move. I've watched patients bring supplement bottles to their dialysis sessions and ask me if they should keep taking them.
I need you to understand exactly why most of them fail.
They use the wrong plant.
The cinnamon in your spice cabinet and in most capsules is Cassia. It looks the same. It smells similar. It is a completely different species with a completely different chemical makeup. At the doses required to move blood sugar, Cassia silently burdens your liver. The European Food Safety Authority documented that as little as a quarter teaspoon per day pushes daily coumarin intake past safe limits — and coumarin damages liver tissue at therapeutic doses.
You were not taking the wrong amount.
You were taking the wrong plant.
True Ceylon cinnamon contains 250 times less coumarin. It is the only species appearing in the clinical research showing real metabolic results.
They are catastrophically underdosed.
Clinical trials used concentrated extract equivalent to 6,000 to 7,200mg daily. Most capsules contain 500 to 1,500mg of raw powder. That is not a small gap. That is the difference between a therapeutic dose and a decorative amount.
They use the wrong delivery format.
The active compounds in Ceylon — the ones that wake up GLUT4 transporters — are fat-soluble.
Your cell walls are a double layer of fat molecules. Fat-soluble compounds need fat to pass through them.
A dry powder capsule has no fat.
So the compounds reach your gut, look for a fat carrier to cross the cell wall, find none, and pass straight through without ever reaching the cells that need them.
Your cinnamon did not fail because cinnamon does not work.
It failed because it was never delivered.
The bag that my patient set down on the table next to his chair?
He was taking Metabolae.
True Ceylon cinnamon. Cinnamomum verum, sourced from a single estate in Sri Lanka's Central Province — the original home of true cinnamon, where the tree has been cultivated for over two thousand years. DNA-verified at the species level. An actual Certificate of Analysis, not a label claim.
Dosed at 7,200mg equivalent per softgel. A 12:1 concentrated extract. The dosing range that corresponds directly to the published clinical trials.
Suspended in MCT oil from coconuts. Not as a filler. As the delivery system — the fat bridge that carries the active compounds through your cell wall and into the cells where the GLUT4 transporters have been waiting for years to be told to surface.
Third-party tested. GMP-certified. Every batch verified for purity, potency, and coumarin levels. Made in an FDA-registered facility. Zero fillers.
I ordered a bag that night.
Week 1, the fog lifted. Not managed — lifted. I finished a twelve-hour shift and still had thoughts left. My feet stopped aching after long days on the floor. I slept through the night for the first time in months.
Week 2, my fasting readings — which had been running 135 to 145 — started showing up in the 110s. I checked three times the first morning I saw 108 because I didn't believe it.
Week 4, the readings stabilized in the low 90s. Stable. Consistent. The kind of numbers I had not seen since before any of this started.
Week 8, I pulled my own labs. Creatinine back to 0.8. GFR climbed from 86 to 91.
Week 10, my doctor pulled up my full panel. A1C down from 6.4 to 5.4. Creatinine holding at 0.8. GFR at 94. Seven pounds gone without changing what I ate.
She looked at the numbers. Looked at me.
"What did you change?"
I handed her the research I'd been reading at 11:30 PM for three weeks.
She read for ten minutes. Closed the folder.
"Your kidney function improved."
I nodded.
"Keep doing whatever you're doing."
That patient who set the bag on the table?
He's still on dialysis. That door closed for him a long time ago. But his brother-in-law — the one he told me about — came in with him to a follow-up visit two months later. I met him in the waiting room. A1C 5.9. Creatinine stable. GFR climbing. Not in a chair. Not going to be.
He looked at me and said: "The drain opened."
I've recommended Metabolae to eight patients now. Or to their family members in the monitoring window — the ones who still have a chance.
Every single one has come back and reported the same pattern.
Better sleep within the first week. Steady energy through the day. Lower fasting glucose within the first month.
One woman — 58, A1C 6.9, protein spillage climbing for three years — came back at her 90-day follow-up with spillage down 45 percent. She cried when she told me the foam in her toilet was gone.
Another patient's GFR went from 53 to 59 in four months. His nephrologist, who had been preparing him for the dialysis conversation, told him the trajectory had changed and asked what he had added.
But the one I think about most is Ruth.
I told her what I'd found. She looked at me with tears running down her face and said: "Tell everyone. Don't let them end up like me."
That's why I'm writing this.
If you are sitting in the monitoring window right now — if your A1C is between 6.0 and 7.5, if your doctor keeps saying "we'll keep an eye on it," if your creatinine is creeping up a tenth at a time, if your GFR is dropping a point or two each quarter, if there is foam in your toilet, if your feet tingle — try Metabolae risk-free.
Ninety-day money-back guarantee. No questions asked. If your fasting glucose does not come down, if your kidney markers do not move, if you see no difference in 90 days, you pay nothing.
The patients who see real movement in their kidney function are the ones who committed to at least three months. That is how long it takes to give your GFR a real chance to stabilize and shift. That is how long it takes to move A1C meaningfully.
The 90-day guarantee means those three months cost you nothing if the numbers do not move.
Here is what happens if they do.
Your fasting glucose starts dropping between weeks 2 and 4. Your sleep improves within the first week — most people stop waking multiple times within 5 to 7 days. Your energy levels out through the day. And at your next lab draw — the one where your doctor has been saying "let's keep an eye on it" — she pauses.
Looks at the numbers.
Looks at you.
Asks what you changed.
You tell her.
She uses a word you have not heard in years of appointments.
"Improving."
Not managed.
Improving.
The window stays open. The chair stays empty.
One softgel daily with breakfast. That is the whole protocol.
Metabolae is a small company sourcing verified Ceylon from a single estate in Sri Lanka's Central Province, testing every batch, using a fat-based delivery system that costs more to produce. When a batch sells out it waits on the next harvest. If you click and see out of stock, sign up for the notification. If it is available, order now.
There is a promotion running currently. Three bottles at a significant discount — which is exactly the window for the kidney markers to actually move.
If you are dealing with:
Foam in the toilet that will not go away no matter how many times you flush. Tingling or burning in your feet that your doctor calls neuropathy. Fasting glucose that will not come below 130 no matter what you cut out. Creatinine climbing a tenth at a time every quarter. GFR dropping while your doctor "keeps an eye on it." An A1C your doctor calls "managed" or "prediabetic" while your body keeps sending signals that something is wrong.
Give it 90 days. Track your fasting glucose every morning. Note your sleep, your energy, your feet. Go back for your next labs.
If the numbers do not move, you get your money back.
But if they do — if your kidney markers hold or climb, if the foam stops, if your doctor pauses over your labs and says the word you have been waiting to hear for years — you will understand why I now have a standing conversation with every patient who still has a chance to avoid my chairs.
The doors are closed. The sand is still coming. But the window is still open.
Don't let someone else tell your story with the words "I wish someone had told me sooner."
I just did.
Click below and get Metabolae while it is still available.
~ Sandra Keller, RN, Dialysis Unit, 14 years
👉 https://metabolae.com/products/ceylon-cinnamon-7200mg